Level:
Correct: 0
Incorrect: 0
Marks: 0/0
Exam Practice
Subject:
Topics:
Avg
score:
–
Topics
done:
0/12

The impact of war and technology on surgery

Practise 34 exam-style questions on The impact of war and technology on surgery for AQA GCSE History (Health and the people). Write your answer as you would in the exam and get it marked in seconds against the mark scheme, point by point, with an AI tutor on hand if you get stuck.

  • 34 questions
  • 1–20 marks each
  • Instant marking
  • No sign-up needed
20 questions, marked as you go

Sample questions with model answers

Here are 4 of the questions in this topic, each with a model answer, an explanation of why it earns the marks and the mark scheme an examiner would use.

Question 1

2 marks

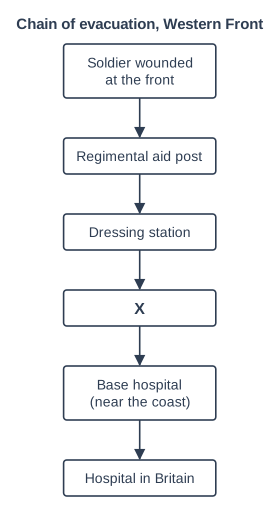
Figure 1 shows the chain of evacuation for a wounded British soldier on the Western Front during the First World War.

What should replace box X? Give one way in which the work done there helped surgery to develop.

Chain of evacuation, Western Front. Flow chart of 6 boxes joined by arrows, read from top to bottom. The first box is "Soldier wounded at the front", which leads to "Regimental aid post", which leads to "Dressing station", which leads to box X, which leads to "Base hospital (near the coast)", which leads to "Hospital in Britain".

Model answer

Box X is the casualty clearing station. These were the first places near the front where major operations could be done, and surgeons there used X-ray machines and blood transfusions, including the stored blood first used at Cambrai in 1917.

Explanation

The chain of evacuation moved wounded men from the front to the regimental aid post, dressing stations, casualty clearing stations, base hospitals and home. The casualty clearing stations, a few miles behind the lines, were where X-rays, transfusions and surgery came together, so they were central to wartime progress in surgery.

Mark scheme
  1. 1 mark

    Box X: the casualty clearing station (CCS).

    Accept: clearing hospital. Do not accept: dressing station (shown), base hospital (shown), field hospital without further detail.

  2. 1 mark

    One way: major operations were carried out there soon after wounding, using X-ray machines to locate bullets and shrapnel; blood transfusions (including stored blood, Cambrai 1917) were given there; surgeons gained great experience of treating wounds (e.g. cleaning wounds and removing damaged tissue to prevent infection); triage of the wounded.

    Any one valid way for 1 mark.

Question 2

8 marks

Source A: one of a series of pastel drawings made in 1916-17 by Henry Tonks, a trained surgeon who had become an artist, of soldiers with facial injuries who were treated by the surgeon Harold Gillies. Tonks made the drawings to record the soldiers' injuries before and after their operations.
This drawing shows the head and shoulders of a young soldier with a severe wound to his face. It is drawn carefully and in detail, in soft colours.

How useful is Source A to an historian studying the impact of the First World War on plastic surgery?
Explain your answer using Source A and your contextual knowledge.

Model answer

Source A is useful because it shows the kind of terrible facial injuries that the First World War produced. Trench warfare meant that soldiers' heads were exposed when they looked over the parapet, and shell fragments and bullets caused huge numbers of face wounds. It was injuries like the one in the drawing that led Gillies to set up a specialist unit at Aldershot in 1916; after the Battle of the Somme about 2,000 men arrived.

The provenance makes the drawing reliable. Tonks had trained as a surgeon, so he understood anatomy and could draw wounds accurately. The drawings were made as medical records for Gillies, not for the public or for propaganda, so there was no reason to hide or exaggerate the injuries. Pastel colours also showed the wounds more clearly than the black-and-white photographs of the time. The fact that an artist was part of the team is itself useful evidence, because it shows Gillies' methodical approach: surgeons, dentists, anaesthetists, photographers and artists worked together, and before-and-after records were used to plan and judge each operation.

However, the source has limits. It shows only one soldier, so it cannot show the scale of Gillies' work, which treated over 5,000 servicemen at the Queen's Hospital, Sidcup. It does not show the techniques that were developed, such as the tubed pedicle of 1917, or how many operations were needed. Nor does it show the result, or the stigma that some disfigured men faced afterwards.

Overall, Source A is useful for showing the injuries caused by the war and the careful, team-based methods of Gillies' unit, but less useful for showing the surgical techniques and their success, so it would need to be used with other evidence such as Gillies' own records.

Explanation

Tonks's pastels were medical records made for Gillies' team, so they are accurate and not propaganda. Level 4 needs a sustained judgement that uses both content (the severity of the injuries) and provenance (a surgeon-artist recording cases for treatment), and recognises what one drawing cannot show (techniques, scale, results).

Mark scheme
  1. 8 marks

    Levels of response (8 marks).
    Level 4 (7-8 marks): Complex evaluation of Source A with a sustained judgement based on content and provenance, e.g. it is useful because a detailed, accurate medical record made by a surgeon-artist working in Gillies' team shows the kind of facial injuries trench warfare caused and the careful, team-based methods of Gillies' unit; but as a record of one man's injury it cannot show the techniques used (such as the tubed pedicle), the results, or the scale of the work; the judgement is supported by accurate contextual knowledge and sustained throughout.
    Level 3 (5-6 marks): Developed evaluation of Source A based on content and/or provenance: explains, with relevant contextual knowledge, how the content and/or the artist, purpose and date make it useful or limited.
    Level 2 (3-4 marks): Simple evaluation of Source A based on content and/or provenance, e.g. useful because it shows a wounded soldier, with little supporting knowledge.
    Level 1 (1-2 marks): Basic analysis of Source A: describes what the drawing shows.
    0 marks: nothing worthy of credit.

    Indicative content (not a checklist; credit other valid points): Content: shows the severity of facial wounds that the war produced (shell fragments and bullets; heads exposed above the parapet in trench warfare). Provenance: Tonks had trained as a surgeon, so he understood anatomy and drew accurately; the drawings were made as medical records for Gillies, not for publication or propaganda, so there was no reason to hide or exaggerate the injuries; colour pastels showed wounds more clearly than the black-and-white photographs of the time; made in 1916-17, when Gillies' unit at Aldershot and then the Queen's Hospital, Sidcup (1917) were treating thousands of men (about 2,000 arrived after the Somme). Shows the team approach: artists, photographers, dentists, anaesthetists and surgeons worked together; drawings and photographs were used to plan operations and record before-and-after results. Limits: shows one soldier, not the scale (over 5,000 servicemen treated at Sidcup); does not show the techniques - skin grafts, flaps, the tubed pedicle (1917) - or how many operations were needed; does not show the outcome or the soldier's later life (stigma, masks for those who could not be helped); does not show the long-term impact (Gillies' 1920 book, training McIndoe, plastic surgery in the Second World War). Possible judgement: useful evidence of the injuries and of Gillies' methodical, team-based approach, but limited for the surgical techniques and results.

Question 3

8 marks

Source A: from a report in a British newspaper, 4 December 1967, the day after the world's first human heart transplant. (Written for practice.)
In a Cape Town operating theatre yesterday, a team of surgeons led by Professor Christiaan Barnard did what was thought impossible only a few years ago. They removed the diseased heart of a 53-year-old grocer and replaced it with the healthy heart of a young woman killed in a road accident. Last night the new heart was beating strongly and the patient was reported to be conscious. Doctors around the world are calling it the greatest operation of the century. The day may soon come when a worn-out heart can be replaced as easily as a worn-out part in a machine.

How useful is Source A to an historian studying the development of transplant surgery?
Explain your answer using Source A and your contextual knowledge.

Model answer

Source A is useful because it gives the basic facts of the first human heart transplant and shows the excitement it caused. Its details are accurate: Barnard's team in Cape Town replaced the diseased heart of Louis Washkansky, a 53-year-old grocer, with the heart of a young woman killed in a road accident, on 3 December 1967. Phrases such as 'the greatest operation of the century' show how the operation was seen as a breakthrough, because the heart had always been regarded as the centre of life. This helps explain why surgeons around the world rushed to copy it, with about 100 heart transplants attempted in 1968, including the first British one in May 1968.

However, the provenance limits its usefulness. It was written the day after the operation, relying on early reports from the hospital, so the journalist could not know what would happen. Washkansky died after only 18 days, of pneumonia, because the drugs used to stop rejection had weakened his immune system. As a newspaper aiming to sell copies, it is also sensational and over-optimistic: the claim that hearts could soon be replaced 'as easily as a worn-out part in a machine' was proved badly wrong. Most early transplant patients died within weeks or months, and in Britain heart transplants were stopped until Papworth resumed them in 1979.

The source also leaves out the wider development of transplant surgery. It does not mention earlier kidney transplants, the first successful one in 1954, or the problem of rejection, which was only overcome when ciclosporin came into use in the early 1980s.

Overall, Source A is useful for showing the moment of breakthrough and the public's optimistic reaction, but its date and purpose make it unreliable as a guide to how successful transplant surgery really was.

Explanation

Barnard's 1967 transplant caused worldwide excitement, but Washkansky died after 18 days and early transplants mostly failed until ciclosporin (1980s). Level 4 needs a sustained judgement weighing the report's accurate facts and evidence of optimism against its provenance (written the next day, sensational) and what it could not know.

Mark scheme
  1. 8 marks

    Levels of response (8 marks).
    Level 4 (7-8 marks): Complex evaluation of Source A with a sustained judgement based on content and provenance, e.g. it is useful because a newspaper report from the day after the operation shows the facts of Barnard's first heart transplant and the huge excitement and optimism it caused; but, written within a day for a mass readership, it exaggerates and could not know that the patient would die after 18 days, that most early transplants failed because of rejection, or that success came only with ciclosporin in the 1980s; the judgement is supported by accurate contextual knowledge and sustained throughout.
    Level 3 (5-6 marks): Developed evaluation of Source A based on content and/or provenance: explains, with relevant contextual knowledge, how the content and/or the nature, purpose and date make it useful or limited.
    Level 2 (3-4 marks): Simple evaluation of Source A based on content and/or provenance, e.g. useful because it was written at the time, with little supporting knowledge.
    Level 1 (1-2 marks): Basic analysis of Source A: describes or paraphrases the report.
    0 marks: nothing worthy of credit.

    Indicative content (not a checklist; credit other valid points): Content: accurate basic facts - Christiaan Barnard, Groote Schuur Hospital, Cape Town, 3 December 1967; patient Louis Washkansky (a 53-year-old grocer) received the heart of a young woman killed in a road accident; shows a team of surgeons; shows the excitement and optimism ('greatest operation of the century'; replacing a heart 'as easily as a worn-out part'). Provenance: a newspaper report written the day after, so it captures immediate reactions, but journalists depended on early reports from the hospital and aimed to sell papers with a dramatic story, so it is sensational and over-optimistic; a British paper reporting events abroad. Limits: written too soon to know the outcome - Washkansky died after 18 days of pneumonia, because anti-rejection drugs weakened his immune system; about 100 transplants were attempted worldwide in 1968, most failing; the first British heart transplant (Donald Ross, May 1968) patient lived about six weeks; transplants in Britain stopped until 1979 (Papworth); ciclosporin from the early 1980s made transplants successful. Does not show earlier foundations (kidney transplants from 1954; British kidney transplant in Edinburgh 1960; heart-lung machines; animal research) or ethical debates (definition of death, brain-stem death criteria 1976, organ donation). Possible judgement: useful for the moment of breakthrough and public reaction, limited for the real progress of transplant surgery.

Question 4

20 marks

Has the role of the individual been the main factor in the development of surgery in Britain?

Explain your answer with reference to the role of the individual and other factors. Use a range of examples from across your study of Health and the people: c1000 to the present day.

[16 marks] [SPaG 4 marks]

Model answer

The history of surgery is full of famous individuals, from Paré to Lister and Gillies, and their determination and skill have been very important. However, I will argue that individuals were not the main factor, because their achievements depended on science and technology and were often made possible by war or government.

In the medieval and early modern periods individuals made important but limited contributions. John of Arderne developed a successful operation for anal fistula and wrote it down in 1376, and in 1403 John Bradmore saved Prince Henry by removing an arrowhead from his face. In the sixteenth century Vesalius corrected Galen's anatomy and Paré used ligatures instead of cauterising and designed artificial limbs. These individuals showed skill and courage in challenging tradition, but the authority of another individual, Galen, together with the problems of pain and infection, meant that surgery changed slowly.

In the eighteenth and nineteenth centuries individuals made breakthroughs that transformed surgery. John Hunter brought an experimental, scientific approach to surgery and taught many surgeons. James Simpson discovered chloroform in 1847 and argued against religious objections to it, and Joseph Lister introduced antiseptic surgery from 1865, persisting despite opposition from other surgeons. Without their determination these advances might have been delayed.

In the twentieth century individuals were again important. Harold Gillies developed plastic surgery in the First World War, Archibald McIndoe transformed the treatment of burns in the Second, John Charnley developed the hip replacement in 1962 and Christiaan Barnard carried out the first heart transplant in 1967.

However, almost every one of these individuals depended on other factors. Lister's work was only possible because of Pasteur's germ theory and the chemical carbolic acid; Simpson built on the chemistry that had produced ether. Gillies and McIndoe developed their methods because war produced thousands of patients with terrible injuries, and Paré too was an army surgeon. Barnard's operation only became truly successful when the anti-rejection drug ciclosporin was developed in the 1980s. Government also mattered: the Anatomy Act of 1832 allowed surgeons to study anatomy legally, and the NHS from 1948 paid for transplants and new technology. Chance played a part, as when Roentgen discovered X-rays in 1895, and communication spread individuals' ideas, through printed books and journals such as The Lancet. In modern surgery, developments such as keyhole surgery, which depended on Harold Hopkins' fibre optics and video cameras, are the work of teams, engineers and companies as much as individual surgeons.

In conclusion, individuals have played a vital role in surgery, because someone had to have the vision to try a new method and the determination to persuade others. But they were not the main factor. Their success depended on science and technology, which provided the knowledge and tools, and on war and government, which provided patients, urgency and money. The greatest advances came when a determined individual was able to use new science in the right circumstances.

Explanation

Individuals such as Paré, Simpson, Lister, Gillies, McIndoe and Barnard drove change, but each depended on science and technology, war, government or chance. A Level 4 essay weighs individuals against these factors with examples from across the whole period and sustains a judgement; SPaG is marked separately.

Mark scheme
  1. 16 marks

    Levels of response (16 marks).
    Level 4 (13-16 marks): Complex explanation of the role of the individual and other factors leading to a sustained judgement about whether individuals have been the main factor in the development of surgery, supported by a range of accurate, specific examples from across the whole period, e.g. explains the contributions of individuals such as Paré, Vesalius, Hunter, Simpson, Lister, Gillies, McIndoe and Barnard (and individuals who held back change, such as Galen and opponents of Lister), weighing them against science and technology, war, government, chance and communication.
    Level 3 (9-12 marks): Developed explanation of the role of the individual and other factor(s), with relevant specific examples from more than one period; there may be a judgement, but it is not fully sustained.
    Level 2 (5-8 marks): Simple explanation of individuals and/or other factor(s), with a limited range of examples or a narrow time span.
    Level 1 (1-4 marks): Basic explanation of one or more factors: general statements or narrative with little relevant knowledge.
    0 marks: nothing worthy of credit.

    Indicative content (not a checklist; credit other valid points): Individuals encouraging change: John of Arderne (fistula operation, 1376); John Bradmore (saved Prince Henry, 1403); Vesalius (anatomy, 1543); Paré (ligatures, artificial limbs, 1537 onwards); Harvey (circulation, 1628); John Hunter (scientific, experimental surgery, 18th century); James Simpson (chloroform, 1847) and John Snow (safe doses); Joseph Lister (antiseptics, 1865-67); Wilhelm Roentgen (X-rays, 1895); Karl Landsteiner (blood groups, 1901); Harold Gillies (plastic surgery, Sidcup 1917); Archibald McIndoe (burns, Guinea Pig Club 1941); John Charnley (hip replacement, 1962); Christiaan Barnard (heart transplant, 1967); Roy Calne (ciclosporin); Godfrey Hounsfield (CT, 1971); Harold Hopkins (fibre optics for keyhole surgery). Individuals inhibiting change: Galen's authority on anatomy for over 1,000 years; surgeons who opposed anaesthetics or Lister's methods. Limits of individuals: they depended on science and technology (germ theory, chemistry, physics, electronics); war gave them patients and urgency (Paré, Gillies, McIndoe); government provided legal and financial support (Anatomy Act 1832; NHS 1948; NBTS 1946); chance (Paré's oil; Roentgen); communication spread their ideas (printing; The Lancet; Gillies' 1920 book); in modern surgery teams, hospitals and companies matter more than lone individuals. Possible judgements: individuals were essential catalysts but depended on other factors; or individuals were the main factor because each breakthrough needed someone with the vision and determination to change practice; or individuals mattered more before 1900, teams and technology since.

  2. 4 marks

    SPaG. High performance (4 marks): spells and punctuates with consistent accuracy; uses rules of grammar with effective control of meaning overall; uses a wide range of specialist terms as appropriate.
    Intermediate performance (2-3 marks): spells and punctuates with considerable accuracy; uses rules of grammar with general control of meaning overall; uses a good range of specialist terms as appropriate.
    Threshold performance (1 mark): spells and punctuates with reasonable accuracy; uses rules of grammar with some control of meaning and any errors do not significantly hinder meaning overall; uses a limited range of specialist terms as appropriate.
    0 marks: the student writes nothing, or the response does not relate to the question, or errors severely hinder meaning.

    SPaG marks are awarded only if the answer relates to the question.

Ready to try the rest? Every answer you write is marked against the mark scheme, so you can see exactly where the marks are.

AI Tutor Hints first, answers after you try

Hi! Stuck? Ask me for a hint and I’ll help you work it out. Once you’ve checked your answer I can explain exactly where the marks are.