Level:
Correct: 0
Incorrect: 0
Marks: 0/0
Exam Practice
Subject:
Topics:
Avg
score:
–
Topics
done:
0/12

A revolution in surgery

Practise 34 exam-style questions on A revolution in surgery for AQA GCSE History (Health and the people). Write your answer as you would in the exam and get it marked in seconds against the mark scheme, point by point, with an AI tutor on hand if you get stuck.

  • 34 questions
  • 2–20 marks each
  • Instant marking
  • No sign-up needed
20 questions, marked as you go

Sample questions with model answers

Here are 4 of the questions in this topic, each with a model answer, an explanation of why it earns the marks and the mark scheme an examiner would use.

Question 1

2 marks

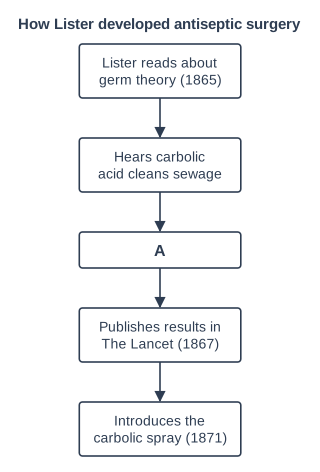
Figure 1 is a flow chart showing how Joseph Lister developed antiseptic surgery.

What should go in box A?

How Lister developed antiseptic surgery. Flow chart of 5 boxes joined by arrows, read from top to bottom. The first box is "Lister reads about germ theory (1865)", which leads to "Hears carbolic acid cleans sewage", which leads to box A, which leads to "Publishes results in The Lancet (1867)", which leads to "Introduces the carbolic spray (1871)".

Model answer

Box A: Lister used dressings soaked in carbolic acid on the compound fracture of James Greenlees, an 11-year-old boy, in August 1865, and the wound healed without becoming infected.

Explanation

Lister learned of Pasteur's germ theory and of carbolic acid's use on sewage, then tested it on James Greenlees' compound fracture in 1865; the wound healed cleanly. He published in The Lancet in 1867 and introduced the carbolic spray in 1871.

Mark scheme
  1. 1 mark

    Lister used carbolic acid (dressings/lint soaked in carbolic acid) on the wound of James Greenlees, an 11-year-old boy with a compound fracture of the leg (August 1865).

    Accept: tried carbolic acid on a patient's open (compound) fracture. The name Greenlees is not required.

  2. 1 mark

    The wound healed without becoming infected (and the leg did not have to be amputated).

    The second mark needs the result.

Question 2

8 marks

Explain the significance of John Snow's work on anaesthetics for surgery in Britain.

Model answer

John Snow's work on anaesthetics was significant first because it made anaesthetics safer. After ether was introduced at the end of 1846 and chloroform in 1847, the biggest danger was the dose: too little and the patient woke up, too much and they could die. In 1848 15-year-old Hannah Greener died under chloroform, which made many people afraid of it. Snow, a London doctor, studied anaesthetics scientifically. He designed inhalers for ether and chloroform that controlled the amount of vapour a patient breathed in, and he worked out how to give the smallest effective dose. This reduced the risk of death and helped surgeons trust anaesthetics.

Second, he was significant because of his most famous patient. In 1853 he gave chloroform to Queen Victoria at the birth of Prince Leopold, and again in 1857 for Princess Beatrice. The Queen wrote that the effect was 'delightful beyond measure'. Once her use of chloroform became known, it became much harder for religious critics to argue that pain relief in childbirth was wrong, and it became fashionable among wealthy women.

In the longer term, Snow was significant because he was one of the first doctors to specialise in anaesthesia. He gave anaesthetics in thousands of operations, and his book On Chloroform and Other Anaesthetics was published in 1858, after his death. Anaesthetics later became a specialist branch of medicine. However, his significance had limits: chloroform was still dangerous and was later replaced, and painless surgery was not safe surgery until Lister tackled infection from 1865.

Explanation

Snow made anaesthesia safer by designing inhalers and calculating doses when overdoses were killing patients, made it respectable by giving chloroform to Queen Victoria (1853, 1857), and helped create anaesthetics as a specialism. Level 4 explains several aspects, short and long term, and recognises limits.

Mark scheme
  1. 8 marks

    Levels of response (8 marks).
    Level 4 (7-8 marks): Complex explanation of aspects of significance: explains, with specific and accurate knowledge, several aspects of the significance of Snow's work on anaesthetics and how it developed over time, e.g. his scientific approach to measuring doses made ether and chloroform safer at a time when overdoses were killing patients; his treatment of Queen Victoria (1853, 1857) made anaesthesia respectable; in the long term he helped make anaesthetics a specialist branch of medicine.
    Level 3 (5-6 marks): Developed explanation of aspects of significance with relevant knowledge, but less range or less sense of short- and long-term significance.
    Level 2 (3-4 marks): Simple explanation of one aspect, e.g. he gave chloroform to Queen Victoria so people trusted it.
    Level 1 (1-2 marks): Basic explanation: general statements about Snow, or confusion with his work on cholera without explaining its relevance.
    0 marks: nothing worthy of credit.

    Indicative content (not a checklist; credit other valid points): Snow, a London doctor, became interested in anaesthesia soon after ether was introduced in late 1846; in 1847 he designed an inhaler to control the dose of ether and published a book on inhaling ether. He studied chloroform scientifically, worked out how the strength of the vapour affected patients and designed a chloroform inhaler, aiming to give the smallest effective dose. This mattered because dosage was the great danger: Hannah Greener died under chloroform in 1848 and other deaths followed, which fuelled opposition. He gave chloroform to Queen Victoria at the births of Prince Leopold (1853) and Princess Beatrice (1857); her approval made pain relief respectable and fashionable, especially in childbirth. He became the leading anaesthetist in London and gave anaesthetics in thousands of operations. His book On Chloroform and Other Anaesthetics was published in 1858, after his death. Long term: he was one of the first doctors to specialise in anaesthesia, which became a specialist branch of medicine (anaesthetists); his careful, scientific method was the same approach he used on cholera (Broad Street, 1854). Limits: chloroform remained dangerous and was later replaced by safer anaesthetics; anaesthetics alone did not make surgery safe because infection (the 'Black Period') was not solved until Lister.

Question 3

8 marks

Explain two ways in which the ideas of the medieval surgeons Hugh and Theodoric of Lucca in the 13th century and aseptic surgery in the late 19th century were similar.

Model answer

One similarity is that both aimed to make wounds heal cleanly, without pus, instead of encouraging infection. In the 13th century most surgeons believed that pus in a wound was a good sign, known as 'laudable pus', and some even tried to encourage it. Hugh of Lucca and his son Theodoric rejected this idea and argued that wounds should be kept clean so that they healed without pus. Aseptic surgery in the 1880s and 1890s had the same aim: to stop germs from reaching the wound at all, so that it healed without any infection. In both cases the surgeons saw pus as a sign that something had gone wrong, not as part of healing.

A second similarity is that both relied on cleanliness to achieve this. Theodoric cleaned wounds with wine, removed any dirt or foreign objects and covered them with clean, dry dressings. Wine contains alcohol, which kills germs, although Theodoric could not have known this. Aseptic surgeons took cleanliness much further, because germ theory and Koch's discovery of the bacteria that infect wounds in 1878 showed them exactly what they were fighting. They sterilised their instruments and dressings with steam, scrubbed their hands and arms, and wore gowns, caps and, from about 1890, rubber gloves. In both periods these ideas went against the practice of most surgeons. Many medieval surgeons continued to encourage pus, and in the late 19th century older surgeons were slow to give up their frock coats and adopt gowns and gloves.

Explanation

Hugh and Theodoric of Lucca (wine, clean dressings, rejecting 'laudable pus') and aseptic surgery (sterilisation, gowns, gloves) both aimed at clean healing through cleanliness, against the usual practice of their time, though only the later surgeons understood germs. Level 4 needs two similarities explained with specific knowledge of both.

Mark scheme
  1. 8 marks

    Levels of response (8 marks).
    Level 4 (7-8 marks): Complex explanation of similarities: explains two ways in which they were similar, each supported by specific, accurate knowledge of both the medieval surgeons and aseptic surgery (e.g. both aimed to keep wounds clean and prevent pus rather than encouraging it; both relied on cleanliness of wounds and dressings; both went against the accepted practice of most surgeons of their time).
    Level 3 (5-6 marks): Developed explanation of similarities: explains one similarity in detail, or two with less precise knowledge of one development.
    Level 2 (3-4 marks): Simple explanation of one similarity with some supporting knowledge.
    Level 1 (1-2 marks): Basic explanation: identifies a similarity or describes one or both with little explanation.
    0 marks: nothing worthy of credit.

    Indicative content (not a checklist; credit other valid points): Preventing pus rather than encouraging it: Hugh of Lucca and his son Theodoric (Italian surgeons, 13th century) argued against the widely held belief that pus ('laudable pus') was a sign of healing and aimed for wounds to heal cleanly without it; aseptic surgery in the 1880s-90s aimed to stop germs reaching the wound at all, so that wounds healed without infection. Cleanliness: Theodoric cleaned wounds with wine (which, being alcoholic, has an antiseptic effect), removed foreign matter and used clean, dry dressings; aseptic surgeons sterilised instruments and dressings with steam (von Bergmann, 1886), scrubbed hands, wore gowns, caps, masks and rubber gloves (Halsted, c1890) and used theatres that could be washed down. Against accepted practice: Theodoric's ideas were rejected by many medieval surgeons, who continued to encourage pus; aseptic methods replaced Lister's antiseptic spray, which many surgeons had only recently accepted, and older surgeons were slow to adopt gowns and gloves. Credit explanation of the key difference (Theodoric worked without knowledge of germs; aseptic surgery was based on germ theory and Koch's identification of wound bacteria in 1878) where it sharpens the similarity.

Question 4

20 marks

Has war been the main factor in the development of surgery in Britain?

Explain your answer with reference to war and other factors. Use a range of examples from across your study of Health and the people: c1000 to the present day.
[16 marks] [SPaG 4 marks]

Model answer

War has been an important factor in the development of surgery, because it produced huge numbers of serious injuries that forced surgeons to find new methods. However, the most important breakthroughs in overcoming pain and infection were made in peacetime, and war usually speeded up and spread developments that depended on science and technology.

There are examples of war encouraging surgery throughout the period. Medieval surgeons gained much of their experience treating battle wounds, such as arrow and sword wounds, and learned to remove arrowheads and stop bleeding with cautery. In the 16th century Ambroise Paré, a French army surgeon, discovered at the siege of Turin in 1537 that a soothing ointment worked better than boiling oil on gunshot wounds, and he promoted ligatures instead of cautery to stop bleeding. In the 18th century John Hunter's experience as an army surgeon informed his work on gunshot wounds.

War had its greatest impact in the 20th century. In the First World War Harold Gillies developed plastic surgery at Sidcup for soldiers with terrible facial injuries, and methods of storing blood were developed so that transfusions could be given near the front line. Mobile X-ray units helped surgeons find bullets and shrapnel. In the Second World War Archibald McIndoe developed new treatments for airmen with severe burns at East Grinstead, and penicillin was mass-produced to prevent infection in wounds. The scale of injuries, and government funding, speeded up these developments enormously.

However, the key breakthroughs of the 19th century happened in peacetime. Ether was first used in Britain in 1846 and Simpson discovered chloroform in 1847 in civilian practice. Lister began using carbolic acid in a Glasgow hospital in 1865, and aseptic surgery developed in hospitals in the 1880s and 1890s. In fact, war sometimes held back new methods: in the Crimean War in 1854 John Hall warned army surgeons against using chloroform.

Science and technology were more fundamental than war. Lister's work depended on Pasteur's germ theory, and the blood transfusions of the First World War depended on Landsteiner's discovery of blood groups in 1901. X-rays were discovered by Röntgen in 1895, by chance, not because of war. After 1945 transplants and keyhole surgery depended on new drugs and technology developed in peacetime. Individuals, such as Simpson and Lister, and government, especially the NHS from 1948, were also important.

In conclusion, war has been an important factor, particularly in the 20th century, when it speeded up the development of plastic surgery and blood transfusion and the use of penicillin. But it has not been the main factor, because the great problems of pain and infection were solved in peacetime by individuals using science, and wartime advances depended on scientific discoveries that had already been made.

Explanation

War speeded up surgery (Paré, Hunter, Gillies, blood storage, McIndoe, penicillin), but anaesthetics, antiseptics and aseptic surgery were developed in peacetime from scientific advances. Level 4 weighs war against science and technology, individuals and government across the period and reaches a sustained judgement.

Mark scheme
  1. 16 marks

    Levels of response (16 marks).
    Level 4 (13-16 marks): Complex explanation of war and other factors (e.g. science and technology, individuals, government, communication, chance, religion), leading to a sustained judgement about whether war was the main factor in the development of surgery; precisely selected examples from across the whole period, which may distinguish between war creating new methods and war speeding up or spreading developments made in peacetime.
    Level 3 (9-12 marks): Developed explanation of war and at least one other factor, with relevant examples from more than one period; a judgement is reached but is not fully sustained.
    Level 2 (5-8 marks): Simple explanation of war and/or other factors with some relevant knowledge; largely descriptive.
    Level 1 (1-4 marks): Basic explanation of one or more factors with limited, general knowledge.
    0 marks: nothing worthy of credit.

    Indicative content (not a checklist; credit other valid points): War encouraging change: medieval surgeons learned much from treating battle wounds such as arrow and sword wounds; Pare's work as an army surgeon (ointment for gunshot wounds, 1537; ligatures; artificial limbs); John Hunter's experience as an army surgeon (1760s) and his work on gunshot wounds; the Crimean War (1854-56) - chloroform used widely by army surgeons, Florence Nightingale's hospital reforms; the Boer War - early use of X-rays in the field; First World War - Harold Gillies' plastic surgery at Sidcup (from 1917), blood transfusion and blood storage (sodium citrate; blood depots, 1917), mobile X-ray units, the Thomas splint (deaths from compound fractures of the thigh fell sharply), shell-shock treatment; Second World War - Archibald McIndoe's work on burns at East Grinstead (the Guinea Pig Club), mass production of penicillin to prevent infection in wounds, the blood transfusion service. War hindering: wars diverted resources and killed doctors; battlefield conditions spread infection. Peacetime developments: anaesthetics (ether 1846, chloroform 1847), Lister's antiseptics (1865) and aseptic surgery (1880s-90s) were developed in civilian hospitals; X-rays discovered by chance (1895); blood groups (1901); transplants (kidney 1954; heart 1967); keyhole surgery (1980s). Other factors: science and technology (germ theory, chemistry, sterilisation, X-rays, antibiotics, immunosuppressants, fibre optics); individuals (Simpson, Snow, Lister, Gillies, McIndoe, Barnard); government (Anatomy Act 1832; NHS 1948; organ donation laws); communication (The Lancet; sharing of wartime experience); chance (Pare running out of oil; Rontgen). Possible judgements: war speeded up surgery dramatically in the 20th century but most key breakthroughs came in peacetime; or war was the main factor for some branches (plastic surgery, blood transfusion) but not for overcoming pain and infection.

  2. 4 marks

    SPaG. High performance (4 marks): spells and punctuates with consistent accuracy; uses rules of grammar with effective control of meaning overall; uses a wide range of specialist terms as appropriate.
    Intermediate performance (2-3 marks): spells and punctuates with considerable accuracy; uses rules of grammar with general control of meaning overall; uses a good range of specialist terms as appropriate.
    Threshold performance (1 mark): spells and punctuates with reasonable accuracy; uses rules of grammar with some control of meaning and any errors do not significantly hinder meaning overall; uses a limited range of specialist terms as appropriate.
    0 marks: the student writes nothing, or the response does not relate to the question, or errors severely hinder meaning.

    SPaG marks are awarded only if the answer relates to the question.

Ready to try the rest? Every answer you write is marked against the mark scheme, so you can see exactly where the marks are.

AI Tutor Hints first, answers after you try

Hi! Stuck? Ask me for a hint and I’ll help you work it out. Once you’ve checked your answer I can explain exactly where the marks are.