Level:
Correct: 0
Incorrect: 0
Marks: 0/0
Exam Practice
Subject:
Topics:
Avg
score:
–
Topics
done:
0/12

Medical progress

Practise 34 exam-style questions on Medical progress for AQA GCSE History (Health and the people). Write your answer as you would in the exam and get it marked in seconds against the mark scheme, point by point, with an AI tutor on hand if you get stuck.

  • 34 questions
  • 1–20 marks each
  • Instant marking
  • No sign-up needed
20 questions, marked as you go

Sample questions with model answers

Here are 4 of the questions in this topic, each with a model answer, an explanation of why it earns the marks and the mark scheme an examiner would use.

Question 1

2 marks

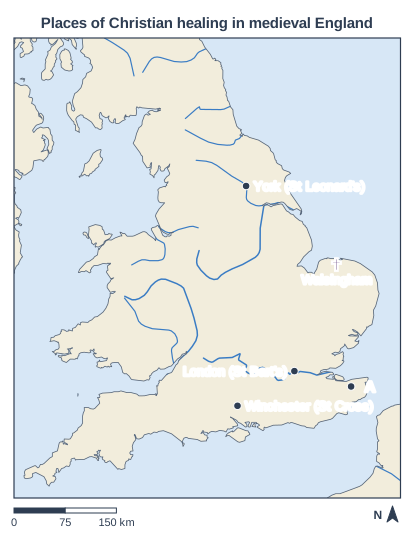
Figure 1 is a map showing some places in medieval England linked to Christian healing. Place A had the most famous shrine in England, visited by the pilgrims in Chaucer's Canterbury Tales.

Name place A. Explain why sick people made pilgrimages to it.

Map of England and Wales, titled "Places of Christian healing in medieval England", drawn with real coastlines (land pale buff, sea pale blue) and no modern borders; a north arrow shows north at the top; the scale bar is 150 km long. Blue lines show rivers. Points: a dot labelled A inland, in the bottom right of the map (about 85% of the way across and 75% of the way down), about 85 km east of the symbol labelled "London (St Bart's)"; a dot labelled "London (St Bart's)" (inland); a dot labelled "Winchester (St Cross)" (inland); a dot labelled "York (St Leonard's)" (inland); a cross symbol (abbey or church) labelled "Walsingham" (inland).

Model answer

Place A is Canterbury. Sick people went there because they believed that if they prayed at the shrine of St Thomas Becket, who was murdered in the cathedral in 1170, the saint would ask God to heal them; many bought 'Canterbury water', thought to contain a trace of his blood.

Explanation

Because illness was often seen as coming from God, prayer, pilgrimage and relics were treatments in their own right. Canterbury and the shrine of Our Lady at Walsingham were the greatest pilgrimage centres in medieval England.

Mark scheme
  1. 1 mark

    Canterbury

    Accept 'Canterbury Cathedral' or 'the shrine of Thomas Becket at Canterbury'.

  2. 1 mark

    They believed that praying at the shrine of St Thomas Becket (murdered there in 1170) would lead God, through the saint, to cure them / that touching relics or drinking 'Canterbury water' containing his blood could heal them

    Accept any valid explanation linked to the saint, relics, prayer or the belief that illness came from God.

Question 2

8 marks

Source A: a summary of an account by John Bradmore, a London surgeon, in his book on surgery written in Latin in the early 1400s.

In 1403, at the Battle of Shrewsbury, Prince Henry (later King Henry V), aged 16, was hit in the face by an arrow beside his nose. The shaft was pulled out, but the arrowhead stayed deep in the bone at the back of his skull. Bradmore widened the wound with probes wrapped in linen soaked in rose honey. He then had a pair of small hollow tongs made, with a screw through the middle, put them into the wound, opened them inside the socket of the arrowhead and drew it out. He washed the wound with white wine, dressed it with ointments every day, and the prince recovered.

How useful is Source A to an historian studying surgery in medieval England?

Explain your answer using Source A and your contextual knowledge.

Model answer

Source A is very useful to an historian studying medieval surgery because it shows what the best surgeons could achieve. Bradmore removed an arrowhead lodged deep in the prince's skull by designing a new instrument, small hollow tongs with a screw, which shows real practical skill and ingenuity. He cleaned the wound with white wine and used rose honey, which we now know are both good at preventing infection, even though nobody in the fifteenth century knew about germs. The daily dressings show careful aftercare. This fits what I know about the practical skill of some medieval surgeons: Theodoric Borgognoni had also recommended cleaning wounds with wine, and war gave surgeons plenty of experience with arrow and sword wounds.

The provenance adds to its value. It is Bradmore's own account, written soon after the event by the expert who carried out the operation, so it is detailed and precise. We also know that it succeeded, because the prince survived to become King Henry V. However, Bradmore wrote it to record his method for other surgeons and to show his skill, so he may have presented it in the best light, leaving out difficulties. The source also leaves things out: it does not mention pain relief, even though dwale existed, and the prince must have suffered greatly.

The biggest limitation is that this was an exceptional case. The patient was the heir to the throne, treated by a leading London surgeon with every resource available. Most surgery in medieval England was minor work, such as bloodletting and lancing boils, carried out by barber-surgeons, and ordinary soldiers rarely received such care; many died from blood loss or infection.

Overall, Source A is very useful for showing the skill and methods of the best medieval surgeons, but it is not typical of surgery as most people experienced it.

Explanation

Bradmore's removal of the arrowhead from Prince Henry in 1403 is a well-documented example of skilled medieval surgery. Level 4 evaluates both content (new instrument, honey and wine, aftercare) and provenance (the surgeon's own account; an exceptional royal case) to judge how typical it is.

Mark scheme
  1. 8 marks

    Levels of response (8 marks).
    Level 4 (7-8 marks): Complex evaluation of Source A that analyses both its content and its provenance (the surgeon's own account, written to record and teach his method) and uses contextual knowledge to reach a sustained judgement, e.g. very useful for showing the skill, ingenuity and practical methods of the best medieval surgeons (honey, wine, new instruments, battlefield experience), but limited because it is an exceptional case with a royal patient described by the surgeon himself.
    Level 3 (5-6 marks): Developed evaluation of content and/or provenance with contextual knowledge, e.g. explains that honey and wine helped to prevent infection, or that Bradmore had reason to present his success.
    Level 2 (3-4 marks): Simple evaluation, e.g. useful because written by the surgeon who did it.
    Level 1 (1-2 marks): Basic analysis, e.g. paraphrases the operation.
    0 marks: nothing worthy of credit.

    Indicative content (not a checklist; credit other valid points): Content: war gave surgeons experience of wounds - arrow wounds were common in battle; Bradmore designed a new instrument for the job, showing practical skill and ingenuity; honey (which we now know is antibacterial) and white wine (alcohol) helped to stop infection, although Bradmore did not know about germs; daily dressings show careful aftercare; the source does not mention pain relief - dwale existed but was dangerous. Context: surgeons were trained by apprenticeship and had lower status than physicians; most surgery was minor (bloodletting, lancing boils, setting bones) and done by barber-surgeons; operations were limited by pain, bleeding and infection; other surgeons, such as Theodoric Borgognoni, also used wine to clean wounds; John of Arderne also wrote about his methods. Provenance: Bradmore's own account, written soon after - detailed, by an expert; written in Latin to record his method for other surgeons and to show his skill, so he may present it in the best light; the patient's survival is confirmed by Henry's later life as king; but it is an exceptional case - a royal patient treated by a leading surgeon with every resource; ordinary soldiers rarely received such care and many died of wounds and infection. Judgement: e.g. very useful for what the best medieval surgery could achieve, less useful for typical surgery.

Question 3

8 marks

Explain two ways in which hospitals in medieval England and the voluntary hospitals of the 18th century were similar.

Model answer

One way in which hospitals in the two periods were similar is that both were founded and paid for by charity from wealthy people, not by the government. In medieval England, kings, bishops, nobles and merchants founded hospitals as an act of Christian charity and to help their souls; St Bartholomew's in London was founded by Rahere in 1123. In the eighteenth century the new voluntary hospitals, such as Westminster (1720), Guy's (1724) and the London Hospital (1740), were also founded and run by wealthy benefactors and subscribers. Thomas Guy, a rich London bookseller, left a fortune to build Guy's Hospital. In both periods hospitals depended on the generosity of individuals, and the government took no responsibility for them.

A second similarity is that both kinds of hospital were selective about whom they admitted. Many medieval hospitals refused lepers, the insane, pregnant women and those who could not be cured, partly from fear of infection and because places were limited, and patients had to leave once they were well. Eighteenth-century voluntary hospitals also usually refused patients with infectious diseases, the incurable, pregnant women and young children, and patients often needed a letter of recommendation from a subscriber to be admitted. In both periods hospitals were mainly for the 'deserving' poor who could be helped to recover, while the wealthy were treated at home.

These similarities show that, even after the dissolution of the monasteries, the idea of the charitable hospital continued for centuries, although by the eighteenth century physicians and surgeons worked in hospitals and trained students there. Hospital care only became a responsibility of the state with the NHS in 1948.

Explanation

Medieval and 18th-century voluntary hospitals were both charitable foundations (not government) and both excluded the infectious and incurable. Level 4 needs two similarities, each supported with specific examples from both periods.

Mark scheme
  1. 8 marks

    Levels of response (8 marks).
    Level 4 (7-8 marks): Complex explanation of two similarities, each supported by specific, accurate knowledge of both medieval hospitals and 18th-century voluntary hospitals, e.g. both were founded and paid for by charity from wealthy people, and both were selective about whom they admitted, excluding the infectious and incurable.
    Level 3 (5-6 marks): Developed explanation of one similarity with specific knowledge of both, or two similarities explained more simply.
    Level 2 (3-4 marks): Simple explanation of one similarity, e.g. both were for the poor.
    Level 1 (1-2 marks): Basic explanation, e.g. both looked after sick people.
    0 marks: nothing worthy of credit.

    Indicative content (not a checklist; credit other valid points): Charity: medieval hospitals were founded by kings, bishops, nobles and merchants as an act of Christian charity and to help their souls (e.g. St Bartholomew's, founded by Rahere in 1123); 18th-century voluntary hospitals (Westminster 1720, Guy's 1724, St George's 1733, the London Hospital 1740) were founded and run by wealthy benefactors and subscribers, e.g. Thomas Guy, who left a fortune to build Guy's; neither was paid for by the government. Selective admission: medieval hospitals often refused lepers, the insane, pregnant women and the incurable; voluntary hospitals usually refused infectious patients, the incurable, pregnant women and young children, and patients often needed a letter of recommendation from a subscriber. For the poor: in both periods the wealthy were treated at home and hospitals served the deserving poor. Religion: both had religious elements (medieval hospitals were religious houses; voluntary hospitals had chaplains and moral rules). Differences may be noted only to support the similarities: by the 18th century physicians and surgeons treated patients and trained students in hospitals.

Question 4

20 marks

Has the role of the individual been the main factor in the development of medical treatment in Britain since c1000?

Explain your answer with reference to the role of the individual and other factors. Use a range of examples from across your study of Health and the people: c1000 to the present day.

[16 marks] [SPaG 4 marks]

Model answer

Individuals have been very important in the development of medical treatment, because many of the greatest new treatments are linked to particular people. However, individuals rarely succeeded alone: their ideas depended on science and technology, on communication, and often on war and government to turn them into treatments that reached patients. So individuals were important, but not the main factor on their own.

In the Middle Ages treatment was shaped by individuals who had lived long before. Hippocrates and Galen created the Theory of the Four Humours, so medieval physicians treated patients by bleeding, purging and using Galen's Theory of Opposites. Islamic individuals such as al-Razi and Ibn Sina added to this knowledge, and Ibn Sina's Canon of Medicine was used in European universities for centuries. This shows that individuals could hold treatment back as well as move it forward, because their authority discouraged new ideas. Religion was equally important in this period: prayer, pilgrimage and the king's touch were seen as treatments, and the Church supported Galen.

From the sixteenth century individuals began to change treatment. Ambroise Paré found a better way to treat gunshot wounds in 1537. Edward Jenner developed vaccination against smallpox in 1796, James Simpson discovered chloroform in 1847, and Joseph Lister introduced antiseptic surgery in 1865. In 1909 Paul Ehrlich's team found Salvarsan 606, the first 'magic bullet' to cure a disease, syphilis.

However, other factors were often decisive. Jenner's vaccination only became widespread when the government made it compulsory in 1853, and it spread quickly because Jenner published his findings in 1798. Lister built on Pasteur's germ theory and published his methods in The Lancet. Ehrlich's success came from science and technology - chemical dyes and the systematic testing of hundreds of compounds - rather than from one person's inspiration.

The story of penicillin shows this most clearly. Alexander Fleming noticed mould killing bacteria in 1928 - an individual's discovery, helped by chance - but he could not turn it into a usable drug. Howard Florey and Ernst Chain did so between 1938 and 1941, but only war made mass production possible: the British and American governments backed it, and American factories produced enough for the D-Day landings in 1944. Since 1948 the NHS has made treatments free, and today new drugs come from large research teams and pharmaceutical companies rather than lone individuals.

In conclusion, individuals such as Jenner, Lister, Ehrlich and Fleming were vital, because they made the key breakthroughs in treatment. But they depended on science and technology to make their discoveries, on communication to spread them, and on war and government to turn them into treatments for ordinary people. Individuals were therefore an important factor, but science and technology, working with government, was more important across the whole period.

Explanation

Individuals (Galen, Ibn Sina, Paré, Jenner, Simpson, Lister, Ehrlich, Fleming, Florey and Chain) made the key breakthroughs, but each depended on science, communication, war or government. Level 4 needs a sustained judgement weighing individuals against these factors with examples from across the period.

Mark scheme
  1. 16 marks

    Levels of response (16 marks).
    Level 4 (13-16 marks): Complex explanation of the role of individuals and of other factors in the development of medical treatment, leading to a sustained judgement about whether individuals were the main factor, supported by a range of accurate, specific examples from across the whole period.
    Level 3 (9-12 marks): Developed explanation of the role of individuals and at least one other factor, with relevant examples from more than one period.
    Level 2 (5-8 marks): Simple explanation of individuals or of other factors, e.g. describes Fleming's discovery of penicillin, with limited examples.
    Level 1 (1-4 marks): Basic explanation; general statements with little specific knowledge.
    0 marks: nothing worthy of credit.

    Indicative content (not a checklist; credit other valid points): Individuals: Hippocrates and Galen - treatments based on the humours (bleeding, purging, the Theory of Opposites) dominated medieval treatment; Islamic doctors - al-Razi, Ibn Sina (Canon of Medicine); John Bradmore and John of Arderne; Paré (1537); Edward Jenner - vaccination (1796, published 1798); James Simpson - chloroform (1847); Joseph Lister - antiseptics (1865); Paul Ehrlich - Salvarsan 606 (1909), the first 'magic bullet'; Alexander Fleming (1928), Howard Florey and Ernst Chain (1938-41) - penicillin. Religion: prayer, pilgrimage, the king's touch as medieval treatments; Church backing for Galen. Science and technology: laboratory methods, chemical dyes, the systematic testing of drugs (Prontosil, 1930s), mass production of drugs, modern pharmaceutical research, transplants, gene therapy. War: the Second World War - British and American government funding and US mass production of penicillin for D-Day (1944). Government: the Vaccination Act (1853) made smallpox vaccination compulsory; the NHS (1948) made treatment free; NICE decides which treatments the NHS uses. Communication: printing, journals (Lister in The Lancet), Fleming's 1929 paper read by Florey and Chain. Chance: Paré, Fleming. Judgement: e.g. individuals made the breakthroughs, but they depended on science, war, government and communication; or individuals like Galen held treatment back as well as moving it forward.

  2. 4 marks

    SPaG. High performance (4 marks): spells and punctuates with consistent accuracy; uses rules of grammar with effective control of meaning overall; uses a wide range of specialist terms as appropriate.
    Intermediate performance (2-3 marks): spells and punctuates with considerable accuracy; uses rules of grammar with general control of meaning overall; uses a good range of specialist terms as appropriate.
    Threshold performance (1 mark): spells and punctuates with reasonable accuracy; uses rules of grammar with some control of meaning and any errors do not significantly hinder meaning overall; uses a limited range of specialist terms as appropriate.
    0 marks: the student writes nothing, or the response does not relate to the question, or errors severely hinder meaning.

    SPaG marks are awarded only if the answer relates to the question.

Ready to try the rest? Every answer you write is marked against the mark scheme, so you can see exactly where the marks are.

AI Tutor Hints first, answers after you try

Hi! Stuck? Ask me for a hint and I’ll help you work it out. Once you’ve checked your answer I can explain exactly where the marks are.