Level:
Correct: 0
Incorrect: 0
Marks: 0/0
Exam Practice
Subject:
Topics:
Avg
score:
–
Topics
done:
0/12

Modern public health

Practise 34 exam-style questions on Modern public health for AQA GCSE History (Health and the people). Write your answer as you would in the exam and get it marked in seconds against the mark scheme, point by point, with an AI tutor on hand if you get stuck.

  • 34 questions
  • 2–20 marks each
  • Instant marking
  • No sign-up needed
20 questions, marked as you go

Sample questions with model answers

Here are 4 of the questions in this topic, each with a model answer, an explanation of why it earns the marks and the mark scheme an examiner would use.

Question 1

2 marks

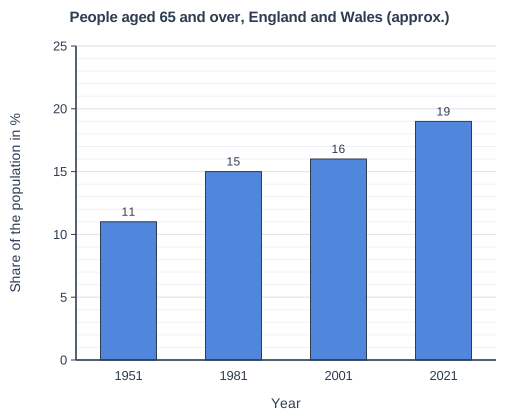
Figure 1 shows the approximate percentage of the population of England and Wales aged 65 and over, 1951-2021.

Give two reasons why this change has increased the pressure on the NHS in the 21st century.

People aged 65 and over, England and Wales (approx.). Bar chart of share of the population in % for each year: 1951 11, 1981 15, 2001 16, 2021 19.

Model answer

Older people are more likely to have long-term conditions such as heart disease, diabetes and dementia, often several at once, which need continuing treatment and expensive medicines. They also need more operations, such as hip replacements, and longer stays in hospital, and beds are blocked when there is not enough social care for them to go home.

Explanation

The share of people aged 65 and over has risen from about 11% in 1951 to about 19% in 2021, partly because of the success of the NHS and better living standards. An ageing population, together with expensive new treatments and lifestyle diseases, is a major reason for the rising cost of healthcare in the 21st century.

Mark scheme
  1. 1 mark

    Older people are more likely to have long-term (chronic) conditions, often several at once - such as heart disease, diabetes, dementia and arthritis - which need continuing treatment and medicines.

    One mark per reason, max 2.

  2. 1 mark

    Older people need more operations and hospital care (e.g. hip and knee replacements, cataract operations, longer hospital stays), which is expensive.

    Accept: more visits to GPs / more emergency admissions.

  3. 1 mark

    Hospital beds are blocked when elderly patients cannot be discharged because there is not enough social care in the community; also free prescriptions for over-60s and a smaller share of working-age taxpayers to fund the NHS.

    Any valid reason linked to an ageing population. Max 2 marks in total.

Question 2

8 marks

Explain two ways in which the Public Health Act of 1848 and the Liberal social reforms of 1906-1911 were similar.

Model answer

One similarity is that both were government responses to investigations that showed a link between poverty and ill-health. The 1848 Public Health Act followed Edwin Chadwick's Report on the Sanitary Condition of the Labouring Population of 1842, which showed that poor people in industrial towns died far younger than the rich - in Liverpool, labourers died on average at about 15 and the gentry at about 35 - and argued that preventing disease would reduce the cost of poor relief. The cholera epidemic of 1848 added urgency. In the same way, the Liberal reforms followed Booth's and Rowntree's surveys, which showed that about 30% of people in London and York lived in poverty, mainly because of low wages, sickness and old age, and the Boer War, which revealed that many recruits were unfit. In both cases evidence gathered by investigators made it harder for governments to argue that health was a purely private matter.

A second similarity is that both were limited, because of laissez-faire beliefs, cost and opposition. The 1848 Act created a General Board of Health, but towns only had to set up local boards of health if their death rate was above 23 per 1,000; many did nothing, and the Board was abolished in 1858. Opponents, nicknamed the 'dirty party', disliked central interference and higher rates. Similarly, the 1906 Act allowed councils to provide free school meals but did not force them to, old age pensions of 1908 went only to the over-70s on low incomes, and the National Insurance Act of 1911 did not cover workers' families or hospital treatment. The Liberals also faced opposition, from the House of Lords, which rejected the People's Budget in 1909, and from doctors who disliked National Insurance. In both cases the government took a step away from laissez-faire, but only a cautious one.

Explanation

The 1848 Public Health Act (after Chadwick's 1842 report) and the Liberal reforms (after Booth, Rowntree and the Boer War) were both responses to evidence linking poverty and ill-health, and both were limited by laissez-faire attitudes, cost and opposition. Level 4 needs two developed similarities supported by specific knowledge of both.

Mark scheme
  1. 8 marks

    Levels of response (8 marks).
    Level 4 (7-8 marks): Complex explanation of similarities: explains two similarities between the 1848 Public Health Act and the Liberal reforms, each supported with specific knowledge of both, and analyses why they were similar (e.g. both were government responses to investigations that linked poverty and ill-health, and both were limited because of laissez-faire attitudes, cost and opposition).
    Level 3 (5-6 marks): Developed explanation of similarities: explains one or two similarities with relevant specific knowledge of both.
    Level 2 (3-4 marks): Simple explanation of one similarity, with some knowledge of both, e.g. both were government action to improve health.
    Level 1 (1-2 marks): Basic explanation: identifies a similarity, or describes one or both, with little comparison.
    0 marks: nothing worthy of credit.

    Indicative content (not a checklist; credit other valid points): Both followed investigations that linked poverty and ill-health: Edwin Chadwick's Report on the Sanitary Condition of the Labouring Population (1842) showed that the poor in industrial towns died much younger than the rich (e.g. in Liverpool labourers' average age at death about 15, gentry about 35) and argued that preventing disease would cut the cost of poor relief; the cholera epidemic of 1848 added urgency. Booth (London, about 30% in poverty) and Rowntree (York, 27.84%) showed poverty was caused by low wages, sickness and old age; the Boer War showed recruits were unfit. Both were limited, permissive or partial because of laissez-faire beliefs and cost: the 1848 Act set up a General Board of Health, but local boards of health were only compulsory where the death rate was above 23 per 1,000; most towns did nothing and the Board was abolished in 1858. The Education (Provision of Meals) Act 1906 allowed but did not require councils to provide school meals; pensions (1908) only for over-70s on low incomes; National Insurance (1911) covered only some workers and not their families or hospital treatment. Both faced opposition from those who disliked interference and higher costs: in 1848 ratepayers, water companies and 'the dirty party' (The Times wrote in 1854 that it preferred to take its chance with cholera than be 'bullied into health'); in 1909-11 the House of Lords rejected the People's Budget, doctors (BMA) objected to National Insurance and some workers resented compulsory contributions. Both marked steps away from laissez-faire towards state responsibility for health. Credit differences only where used to explain the similarity.

Question 3

8 marks

Source A: from a leaflet sent by the government to every household in Britain in 1948, before the National Health Service began.
'Your new National Health Service begins on 5th July. What is it? How do you get it? It will provide you with all medical, dental, and nursing care. Everyone - rich or poor, man, woman or child - can use it or any part of it. There are no charges, except for a few special items. There are no insurance qualifications. But it is not a "charity". You are all paying for it, mainly as taxpayers, and it will relieve your money worries in time of illness.'

How useful is Source A to an historian studying the creation of the National Health Service?
Explain your answer using Source A and your contextual knowledge.

Model answer

Source A is useful because it sets out the founding principles of the NHS in the government's own words. It promises 'all medical, dental, and nursing care' - a comprehensive service - for 'everyone - rich or poor, man, woman or child', with 'no charges' and 'no insurance qualifications'. This was a huge change. Under the 1911 National Insurance scheme only insured workers had free GP treatment, not their wives and children, and many people avoided doctors because they could not afford the fees. The statement that it is paid for 'mainly as taxpayers' shows that the NHS was funded through taxation, and the insistence that it was 'not a charity' shows the government's wish to remove the shame associated with the Poor Law and charity hospitals.

The provenance adds to its usefulness. It is an official leaflet sent to every household, so it shows exactly what the government promised and how it wanted people to understand the new service. Its purpose was to explain how to use the NHS and to encourage people to register with a family doctor before 5 July 1948.

However, because it is government publicity designed to reassure, it presents only a positive picture. It says nothing about the strong opposition from the British Medical Association - in a 1948 poll most doctors voted against the scheme - or about the concessions Aneurin Bevan made to win them over, such as allowing consultants to keep private patients. It also cannot show what happened next: demand was enormous, with millions receiving dental treatment and glasses in the first year, costs were far higher than expected, and charges were soon introduced for dentures and spectacles in 1951 and prescriptions in 1952. The phrase 'except for a few special items' hints that the service was never entirely free.

Overall, Source A is very useful for the principles and public presentation of the NHS, but less useful for the political struggle behind its creation and its early problems.

Explanation

The 1948 leaflet sets out the NHS's principles: comprehensive, universal, free at the point of use and funded by taxation. Level 4 needs a sustained judgement weighing this against its purpose (government publicity to inform and reassure) and what it omits (BMA opposition, Bevan's compromises, costs and charges).

Mark scheme
  1. 8 marks

    Levels of response (8 marks).
    Level 4 (7-8 marks): Complex evaluation of Source A with a sustained judgement based on content and provenance, e.g. it is useful because an official leaflet sent to every home sets out the founding principles of the NHS (comprehensive, universal, free at the point of use, paid for through taxation) and shows how the government wanted the public to understand it; but as government publicity designed to inform and reassure, it says nothing of the opposition from doctors, the compromises Bevan made, the structure of the service, or the rising costs that soon led to charges; the judgement is supported by accurate contextual knowledge and sustained throughout.
    Level 3 (5-6 marks): Developed evaluation of Source A based on content and/or provenance: explains, with relevant contextual knowledge, how the content and/or the purpose, audience and date make it useful or limited.
    Level 2 (3-4 marks): Simple evaluation of Source A based on content and/or provenance, e.g. useful because it comes from the government, with little supporting knowledge.
    Level 1 (1-2 marks): Basic analysis of Source A: describes or paraphrases the leaflet.
    0 marks: nothing worthy of credit.

    Indicative content (not a checklist; credit other valid points): Content: gives the start date (5 July 1948); states the key principles - comprehensive ('all medical, dental, and nursing care'), universal ('everyone'), free at the point of use ('no charges'), no insurance qualifications (unlike the 1911 scheme, which covered only workers, not their families), funded mainly through taxation; stresses it is 'not a charity', to remove the stigma of the Poor Law and charity hospitals. Provenance: an official government leaflet sent to every household, so it is authoritative on what the service promised; its purpose was to inform people and encourage them to register with a GP, and to reassure them - so it presents the NHS positively. Context: created by the National Health Service Act (1946) under Aneurin Bevan, Minister of Health, following the Beveridge Report (1942); tripartite structure - hospitals (nationalised, under regional boards), family doctors, dentists and opticians, and local authority services. Limits: does not mention the BMA's opposition (most doctors voting against it in a 1948 poll) or Bevan's concessions (consultants kept private patients; GPs paid per patient rather than salaried); 'except for a few special items' hints at limits; does not show the huge demand (millions of people received dental treatment and glasses in the first year), the costs far above estimates, or the charges that followed (dentures and spectacles 1951, leading to Bevan's resignation; prescriptions 1952). Possible judgement: very useful for the principles and public presentation of the NHS, less useful for the politics of its creation and its early problems.

Question 4

20 marks

Has the role of the individual been the main factor in improving public health in Britain?

Explain your answer with reference to the role of the individual and other factors. Use a range of examples from across your study of Health and the people: c1000 to the present day.

[16 marks] [SPaG 4 marks]

Model answer

Individuals have played a vital role in improving public health, providing the evidence, ideas and leadership behind almost every major reform. However, individuals could rarely make a lasting difference on their own: their ideas only improved public health when government acted on them, often after war, crisis or new science had made action unavoidable.

In the medieval and early modern periods individuals had a limited impact. Abbots organised clean water supplies and drains in monasteries, and Edward III ordered London's streets to be cleaned during the Black Death in 1349, but these were isolated actions based on the belief that bad air caused disease. In 1662 John Graunt used the weekly Bills of Mortality to study patterns of death, an early example of using statistics, but this did not change public health at the time. Edward Jenner's smallpox vaccination of 1796 was a major breakthrough by one man, yet it only became universal when Parliament made it compulsory in 1853.

In the nineteenth century individuals were crucial in providing evidence. Edwin Chadwick's report of 1842 showed that the poor in towns died much younger than the rich and blamed filth and bad drainage. John Snow's investigation of the Broad Street pump in 1854 showed that cholera spread through contaminated water, and Joseph Bazalgette designed the sewers that cleaned up London. However, their limits show the importance of other factors. Chadwick's 1848 Act was weak and permissive, and he was removed from the Board of Health in 1854. Snow's ideas were not widely accepted in his lifetime, and it took Pasteur's germ theory and Koch's identification of the cholera germ in 1883 to prove him right. Bazalgette's sewers were only built because the Great Stink of 1858 forced Parliament to pay for them.

In the twentieth century individuals again provided ideas and leadership. Booth and Rowntree measured poverty, Lloyd George drove the Liberal reforms, Beveridge's report of 1942 set out a plan to defeat the five giants, and Aneurin Bevan created the NHS in 1948 despite opposition from doctors. Richard Doll and Austin Bradford Hill showed in 1950 that smoking caused lung cancer. Yet war created the conditions in which Beveridge's ideas became popular, Labour's victory in 1945 gave Bevan the power to act, and government provided the money and laws. Communication also mattered: Beveridge's report became a best-seller, and Snow's map and Chadwick's report persuaded others.

In conclusion, individuals have been very important, because without people like Chadwick, Snow, Beveridge and Bevan many reforms would have been delayed. But they were not the main factor. Their ideas only improved public health when government turned them into laws and paid for them, and government usually acted only when war, crisis, science or the votes of ordinary people pushed it. The greatest improvements came when determined individuals and government worked together.

Explanation

Individuals such as Chadwick, Snow, Bazalgette, Booth, Rowntree, Lloyd George, Beveridge and Bevan provided evidence, ideas and leadership, but usually needed government action, often prompted by war, crisis or science, to make lasting change. Level 4 needs a sustained judgement across the whole period; SPaG is marked separately.

Mark scheme
  1. 16 marks

    Levels of response (16 marks).
    Level 4 (13-16 marks): Complex explanation of the role of the individual and other factors leading to a sustained judgement about whether individuals have been the main factor in improving public health, supported by a range of accurate, specific examples from across the whole period, e.g. explains the contributions of individuals such as Jenner, Chadwick, Snow, Bazalgette, Booth, Rowntree, Lloyd George, Beveridge and Bevan, and weighs them against government, science and technology, war, communication and chance, recognising that individuals usually needed government action to make a lasting difference.
    Level 3 (9-12 marks): Developed explanation of the role of the individual and other factor(s), with relevant specific examples from more than one period; there may be a judgement, but it is not fully sustained.
    Level 2 (5-8 marks): Simple explanation of individuals and/or other factor(s), with a limited range of examples or a narrow time span.
    Level 1 (1-4 marks): Basic explanation of one or more factors: general statements or narrative with little relevant knowledge.
    0 marks: nothing worthy of credit.

    Indicative content (not a checklist; credit other valid points): Medieval: abbots and monks organised clean water and drains in monasteries; kings such as Edward III ordered streets cleaned (1349). 17th century: John Graunt used the Bills of Mortality to study deaths (1662). Jenner's smallpox vaccination (1796) - made compulsory in 1853. Edwin Chadwick's report (1842) linked filth, poverty and disease and led to the Public Health Act (1848). John Snow's investigation of the Broad Street pump (1854) showed cholera spread through water. Joseph Bazalgette built London's sewers after 1858. Florence Nightingale used statistics to promote hygiene. Charles Booth (from 1889) and Seebohm Rowntree (1901) measured poverty. David Lloyd George drove the Liberal reforms (pensions 1908, People's Budget 1909, National Insurance 1911). William Beveridge's report (1942); Aneurin Bevan created the NHS (1948). Richard Doll and Austin Bradford Hill linked smoking to lung cancer (1950). Limits of individuals: Chadwick's 1848 Act was weak and he was removed in 1854; Snow's ideas were not widely accepted until after his death (1858); individuals needed government to act (1875 Public Health Act; Welfare State); science (germ theory 1861, Koch 1883) proved what Snow suggested; war created the conditions for Beveridge and Bevan; communication spread their findings; chance (the Great Stink) helped Bazalgette; democracy (Reform Acts 1867, 1884, 1918) and the rise of Labour pushed governments. Possible judgements: individuals were essential in providing evidence, ideas and leadership, but government was the main factor because only it could turn their ideas into national improvements; or individuals were the main factor because almost every major reform can be traced to a particular person.

  2. 4 marks

    SPaG. High performance (4 marks): spells and punctuates with consistent accuracy; uses rules of grammar with effective control of meaning overall; uses a wide range of specialist terms as appropriate.
    Intermediate performance (2-3 marks): spells and punctuates with considerable accuracy; uses rules of grammar with general control of meaning overall; uses a good range of specialist terms as appropriate.
    Threshold performance (1 mark): spells and punctuates with reasonable accuracy; uses rules of grammar with some control of meaning and any errors do not significantly hinder meaning overall; uses a limited range of specialist terms as appropriate.
    0 marks: the student writes nothing, or the response does not relate to the question, or errors severely hinder meaning.

    SPaG marks are awarded only if the answer relates to the question.

Ready to try the rest? Every answer you write is marked against the mark scheme, so you can see exactly where the marks are.

AI Tutor Hints first, answers after you try

Hi! Stuck? Ask me for a hint and I’ll help you work it out. Once you’ve checked your answer I can explain exactly where the marks are.